


Abstract
Objective. A cross-sectional study was undertaken to determine the prevalence of axial gout in patients with established gouty arthritis and to analyze clinical, laboratory, and radiological correlations.
Methods. Forty-eight subjects with a history of gouty arthritis (American College of Rheumatology criteria) for ≥ 3 years under poor control were included. Subjects underwent history, physical examination, laboratory testing, and imaging studies, including radiographs of the hands and feet and computerized tomography (CT) of the cervical and lumbar spines and sacroiliac joints (SIJ). Patients with characteristic erosions and/or tophi in the spine or SIJ were considered to have axial or spinal gout.
Results. Seventeen patients (35%) had CT evidence of spinal erosions and/or tophi, with tophi identified in 7 of the 48 subjects (15%). The spinal location of axial gout was cervical in 7 patients (15%), lumbar in 16 (94%), SIJ in 1 (6%), and more than 1 location in 14 (82%). Duration of gout, presence of back pain, and serum uric acid levels did not correlate with axial gout. Extremity radiographs characteristic of gouty arthropathy found in 21 patients (45%) were strongly correlated with CT evidence of axial gout (p < 0.001). All patients with tophi in the spine had abnormal hand or feet radiographs (p = 0.005).
Conclusion. Axial gout may be a common feature of chronic gouty arthritis. The lack of correlation with back pain, the infrequent use of CT imaging in patients with back pain, and the lack of recognition of the problem of spinal involvement in gouty arthritis suggest that this diagnosis is often missed.
Axial gout is recognized as a known feature of chronic gout1. With the increasing prevalence of hyperuricemia and gout, it is likely that axial gout would be recognized more frequently2. Although literature reviews have described many cases3,4, its prevalence and clinical correlations remain uncertain, as no large, prospective studies have been published. In an earlier analysis of patients with gout who had spinal computerized tomography (CT) available for evaluation, the prevalence of axial gout was 14%1. However, because of its retrospective design, we were not able to derive definitive data on the possible association of axial gout with important clinical and laboratory features including duration of peripheral gouty arthritis; serum urate levels; and presence of clinical or radiological tophi, symptomatic back pain, and comorbidities such as hypertension (HTN), diabetes mellitus (DM), and chronic renal insufficiency.
This cross-sectional study was undertaken to obtain a more accurate estimation of the prevalence of axial gout and to explore its clinical, laboratory, and radiologic correlates.
Similarly to our prior study, CT was utilized as the imaging modality to identify axial gout5. CT reveals characteristic changes of axial gout: intraarticular and juxtaarticular erosions with sclerotic margins and an attenuation or density greater than the surrounding muscle due to deposition of sodium urate crystals. Multiple anatomic sites within the vertebral column can be involved, including the epidural space, intradural space, ligamentum flavum, discovertebral junction, the pedicles, facet joints, spinous processes, filum terminale, and neural foramina5. Other reports have shown biopsy-proven urate crystals in the spine in the presence of characteristic imaging appearance6. Therefore for this study, in the presence of typical CT findings of axial gout in patients with proven clinical gout, biopsy was not obtained to confirm the diagnosis of axial gout. Dual-energy CT is increasingly recognized as a very sensitive tool for identification of monosodium urate deposits in the appendicular skeleton, but has not been systematically applied to the diagnosis of axial gout7.
We hypothesized that axial gout will be seen more commonly in patients with prolonged duration of proven appendicular gout and in patients with radiological evidence of gouty erosions or tophi in the hands or feet. To test this hypothesis, we performed a cross-sectional study in subjects with definite gouty arthritis whose condition was not under optimal control.
MATERIALS AND METHODS
Patients
Patients who satisfied the American College of Rheumatology (ACR) criteria for gout were included in the study from January 2008 to May 20108. All the study-related procedures were performed at Washington Hospital Center and were approved by the institutional review board. Subjects with a history of gout for 3 or more years were recruited if they had at least 1 attack of acute gouty arthritis in the prior year or had persistent hyperuricemia (serum uric acid > 7.0 mg/dl) on a minimum of 3 occasions for 3 years prior to enrollment.
Clinical and laboratory data included duration of peripheral gouty arthritis; past or present back pain; presence of joint deformities from gouty arthritis; presence of clinical tophi; urate crystal demonstration from synovial fluid or tophi; body mass index (BMI); comorbid conditions, namely DM and HTN; current allopurinol therapy; serum uric acid (SUA); and creatinine clearance calculated by the modification of diet in renal disease method.
Imaging studies included radiographs of the hands and feet and low-dose non-contrast CT of the cervical spine, lumbar spine, and sacroiliac joints (SIJ). If prior radiographs of the hands and feet that were available showed erosions or tophi characteristic of gouty change, then no further radiographs were performed. Radiographs were read by an experienced rheumatologist (AW) blinded to CT results. CT were read by 2 musculoskeletal radiologists blinded to clinical data and appendicular radiography results. These radiography and CT results were used in the study. However, the same images (radiographs and CT) were also read by the clinical radiologist in the radiology department assigned to a given patient; the reading was not part of the study but became part of the respective patient’s source document.
Primary and other analyses
Primary analyses included an estimation of the prevalence of axial gout in this population and correlation of axial gout with the duration of peripheral gouty arthritis. Other analyses included spinal location of axial gout and correlation of axial gout with the clinical, laboratory, and radiologic features described above.
Statistical methods
Sample size calculations were based on a frequency of axial gout of 20% in our study population and a mean duration of gout in subjects with axial disease of 13.5 years compared to 9.0 years in those without axial gout. Depending on the estimates of the standard deviations of the duration of gout, sample size estimates for 80% power varied from 40 to 120 patients for nonparametric analyses. We recorded the estimated duration of gout in 5-year increments to > 15 years. Demographic and clinical features were summarized as mean (SD) values for continuous variables and proportions for categorical variables for all subjects and by axial gout status. Fisher’s exact test and Wilcoxon rank-sum test were used to compare the proportion and distribution between the axial groups, respectively. Two-tailed p values < 0.05 were considered statistically significant. Data were analyzed using SAS version 9.1 (SAS Institute, Cary, NC, USA).
RESULTS
Forty-eight subjects were studied. The characteristics of the population are shown in Table 1 and the comparison of those subjects with and without axial gout is shown in Table 2. The gout control was less than optimal, with 96% of research subjects having experienced at least 1 attack of arthritis within the year prior to enrollment. Seventeen of the 48 subjects (35%) had CT evidence of spinal gout with erosions and/or tophi and 7 (15%) had spinal tophi (Figures 1 and 2). The locations of the characteristic CT changes of axial gout were lumbar in 16 (94%), cervical in 7 (42%), and SIJ in 1 (6%). Of the 17 patients with axial gout, 14 (82%) had more than 1 vertebral level involved.

Computerized tomography showing gouty erosions in the lumbar apophyseal joints.
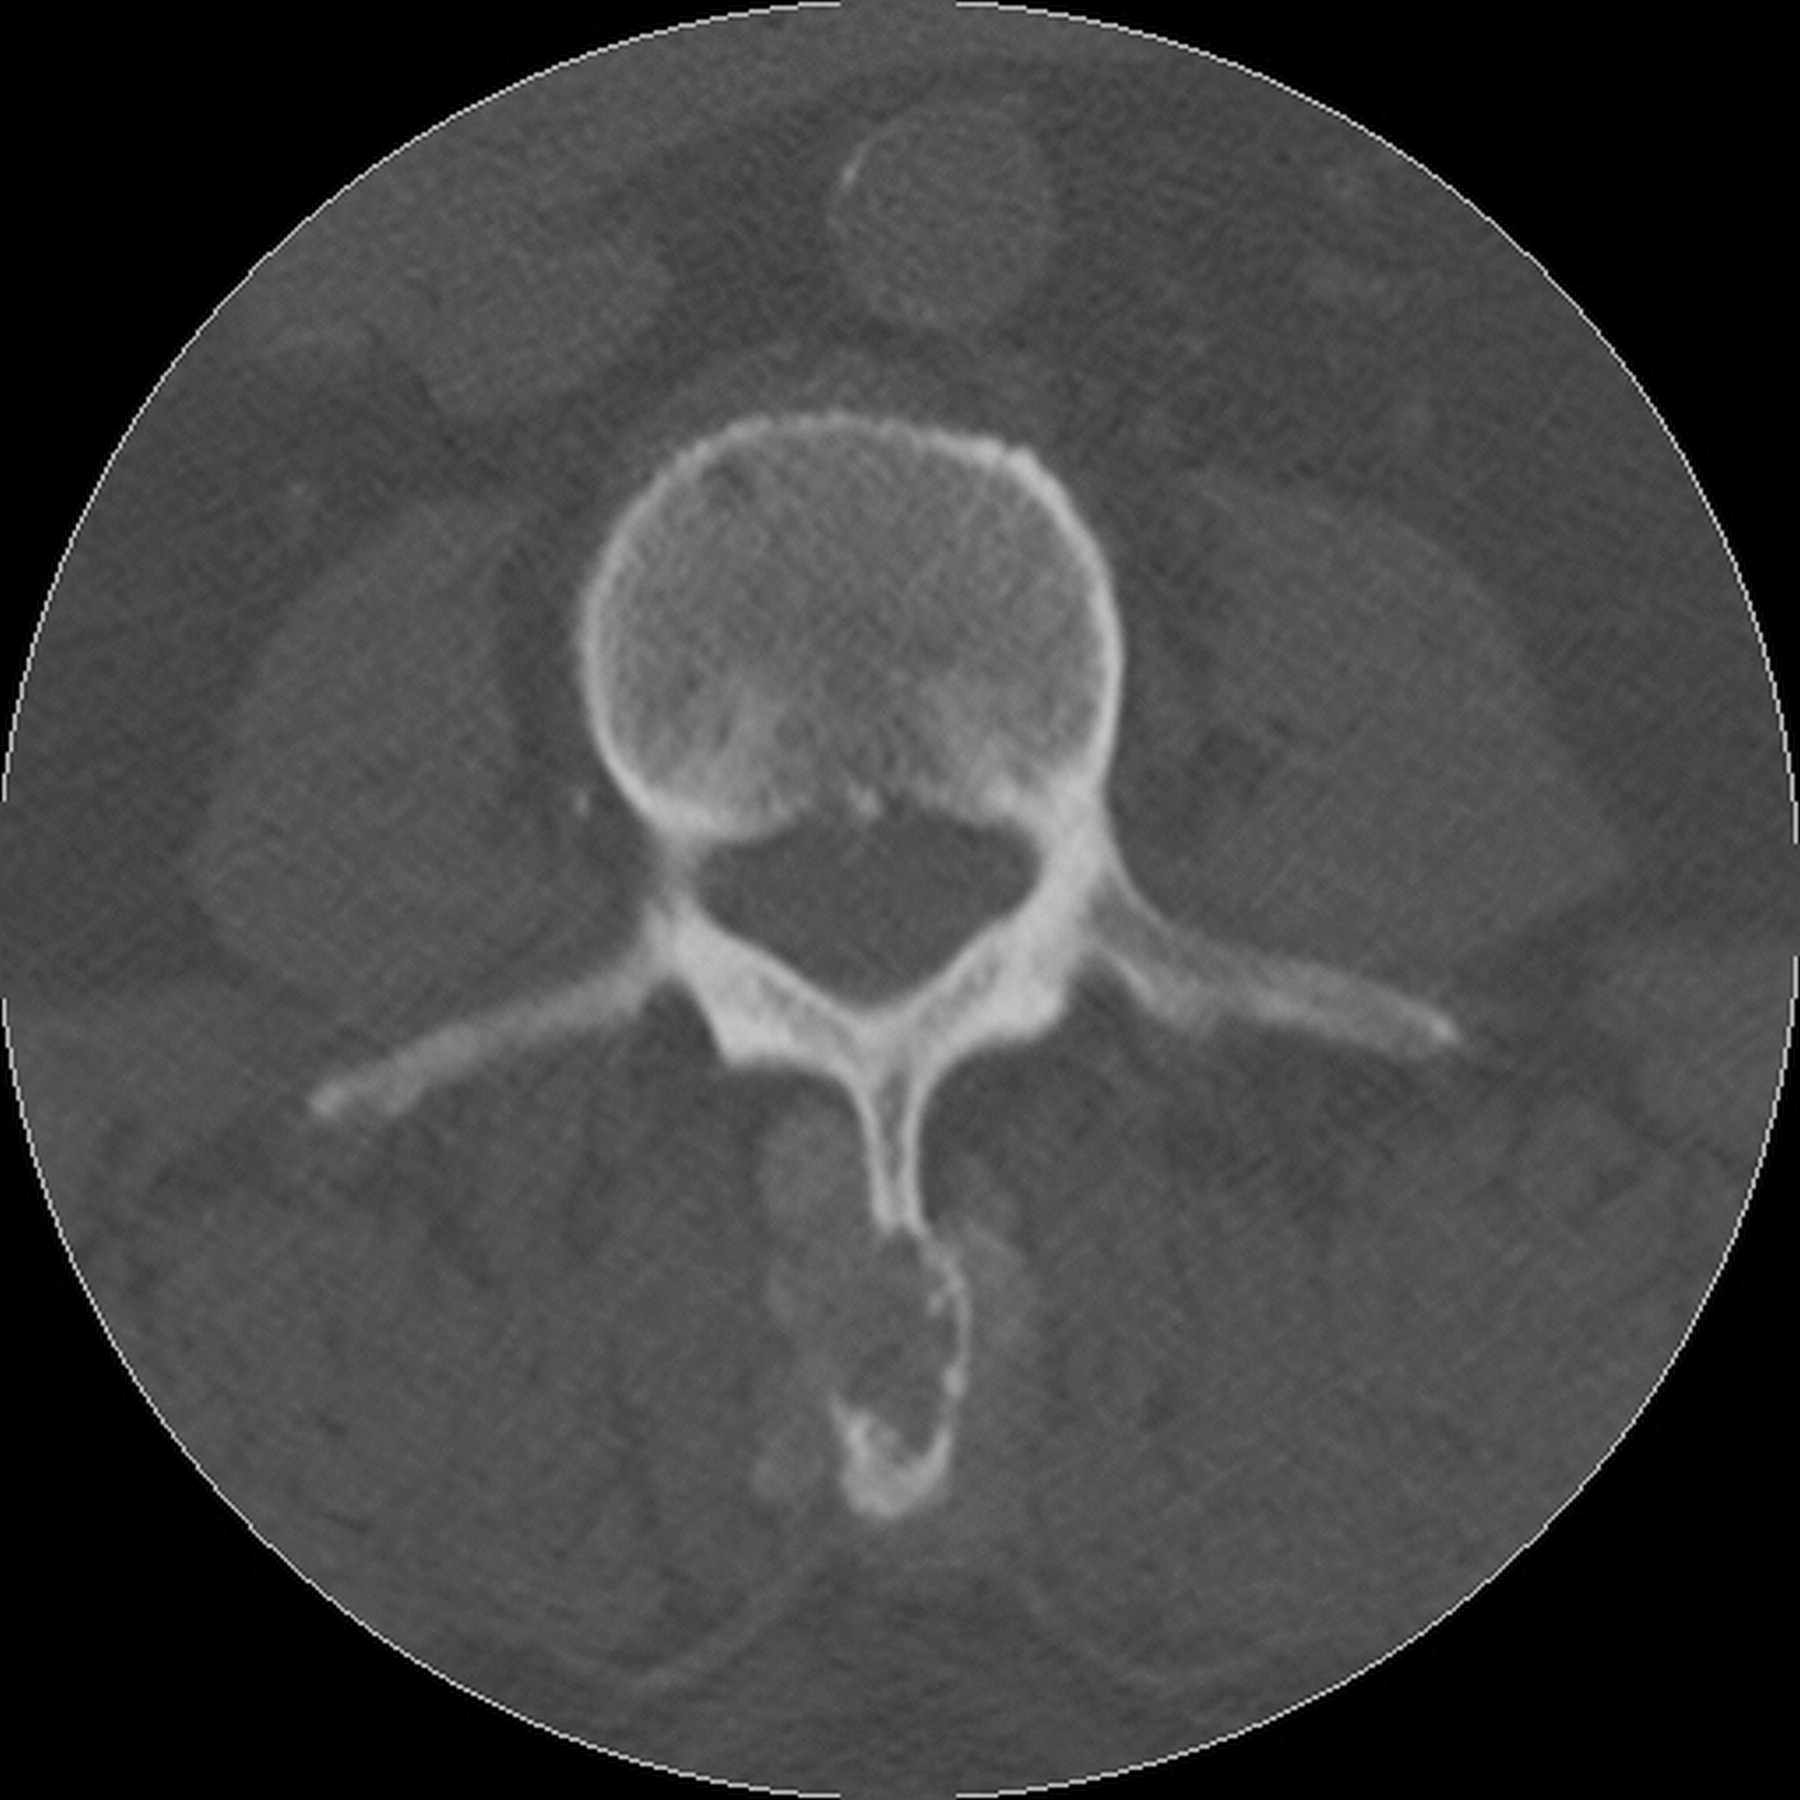
Computerized tomography showing a tophus in the spinous process.
Features of the gout population studied (n = 48 patients).
Features of subjects with and without axial gout.
Men comprised 73% of cases of axial gout compared to women at 27%, but these proportions were similar to the entire gout population studied. The majority (87%) of our study population was black and all the patients with axial gout were black (p = 0.08).
Twenty-six (54%) subjects had gout for more than 10 years and 18 (38%) for more than 15 years. Only 7 subjects (15%) had gout for less than 5 years. While 65% of the subjects with axial gout had clinical gouty arthritis for more than 10 years (compared to 48% of those without axial gout), this was not statistically significant (p = 0.37). There was also no correlation of axial gout with duration of gout when analyzed in 5-year increments. There was no correlation of axial gout with mean SUA and there was a very small difference in mean SUA in those with compared to those without axial gout at the time of CT scanning (Table 2). Clinical tophi were found in 46% of subjects, and 65% of these had evidence of axial gout. This approached but did not reach statistical significance (p = 0.07).
Radiographic gouty changes (erosions and/or tophi) of the hands and/or feet were found in 21 (45%) of 47 subjects (1 patient refused peripheral radiographs) and were highly correlated with CT evidence of axial gout. These radiographic gouty changes were seen in 81% of those with axial gout and only 26% of those without axial gout (p < 0.001). Axial tophi were found on CT in 7 (15%) patients and all had radiographic evidence of peripheral gouty changes (p = 0.005).
There were no correlations of the duration of gouty arthritis (> 10 yrs) with the presence of peripheral tophi or with the presence of radiographic gouty changes.
There was a modest correlation of axial gout with the presence of DM (p = 0.04) but not with high BMI (> 25) or HTN. Ninety-three percent of the subjects with axial gout had a reduced creatinine clearance, but this did not reach statistical significance (p = 0.07). In terms of treatment, 42% of the study subjects were taking current allopurinol therapy with an average dose of 215 mg daily with a range of 50 to 500 mg daily. Among patients who were not currently taking allopurinol, 59% had axial gout, whereas 45% of those taking allopurinol had axial gout (p nonsignificant). The mean dose of allopurinol in those subjects with axial gout was 214 mg daily and in those without axial gout 215 mg daily.
DISCUSSION
In this prospective cross-sectional study we found a prevalence of axial gout of 35%. Although this frequency is surprisingly high, there are features of our study sample that limit generalizability to the entire population of patients with gout. First, we had a disproportionately high number of black subjects in the study, which is representative of our general rheumatic disease population at Washington Hospital Center. Black Americans are known to have a higher prevalence of gout than white Americans; they also have more severe gouty arthritis9,10.
Further, we selected patients whose gout was not under optimal control so that they had either an episode of gouty arthritis in the prior year or persistent hyperuricemia. We specifically studied this population because case reports suggest that axial gout is seen more often in patients with chronic and severe gout11. Other features that indicate that our patients had more severe gout than an unselected population of gout patients are high frequency of a recent attack of gouty arthritis (96%), clinical tophi (46%), and radiographic changes in the hands and/or feet (46%). Despite this severity and a high mean uric acid (7.7 mg/dl), only 42% of subjects were taking urate-lowering therapy, and only 41% of patients with axial gout were taking allopurinol. We surmise that this undertreatment may have contributed to the high frequency of severe gout in this population, including axial gout. Studies have suggested that gout is poorly managed in the population at large, and these study subjects may reflect this problem12. It is not known how representative this is of the gout patients seen in the clinics and practices at our hospital or of patients with gout in general, since the subjects for this research were selected on the basis of lack of optimal control of their gout.
We could not support our primary hypothesis that longer duration of gouty arthritis correlated with the presence of axial gout. However, more than 50% of the study patients had gout for over 10 years and 38% for over 15 years. Therefore, this select population of advanced long-duration gout may not have provided us with a broad enough range of duration to answer that question. Further, because we enrolled about 30 patients fewer than anticipated from our original sample size determinations, a type 2 error is possible. Finally, those factors that lead to deposition of urate in tissues, peripheral joints, and spine may possibly be independent of disease duration once a duration threshold, such as 5 years, has been exceeded. This is supported by our finding that disease duration also did not correlate with clinical tophi or the presence of radiographic erosions in the peripheral joints.
Despite the lack of correlation with disease duration, we found definitive evidence that patients with axial gout — erosions and/or tophi — have severe gout as exemplified by a high correlation with radiological changes of gout in the hands and/or feet. Clinical tophi were also more frequent in subjects with axial gout (65%) compared to 35% without axial gout, and this observation approached statistical significance.
We found no correlation of axial gout with the presence of back pain. However, back pain was common overall (50%), as might be expected in this middle to older aged population, due to the presence of concomitant chronic discogenic disease and osteoarthritis. Case reports have shown that gouty tophi in the spine can cause back pain, nerve root compression, and extremity weakness and in this way mimic other processes, but this was not the case in our population13,14.
Of the 7 subjects with axial gouty tophi by spinal CT, only 3 had back pain and none had radiculopathic symptoms. We do not have sufficient clinical data to determine whether acute back pain would more likely be present in patients with axial gout during a flare of acute gout and become asymptomatic between flares. Patients with acute back pain coincident with acute gouty arthritis who remit on resolution of the acute gout attack have been described11.
Axial gout also did not correlate with higher SUA levels even though the gout was incompletely controlled (recent attack and/or hyperuricemia) in these patients. This discrepancy may be due to the limited availability of consecutive SUA levels for the majority of the subjects; moreover, SUA levels drawn for the study purpose may not be reflective of the mean SUA levels over time. Also, since we selected for poorly controlled gout patients, there may not be a wide distribution of levels, i.e., the mean SUA level for patients with axial gout was 7.5 mg/dl as compared to patients without axial gout (mean SUA 7.9 mg/dl). A study with a larger sample size and a more diverse gout population would elucidate a possible correlation.
Although there was modest correlation of DM with axial gout, similar results were not seen with HTN and high BMI. The reason for this is unclear, since DM, HTN, and increased BMI are all risk factors for gout, and gout is a risk factor for DM15,16. This finding suggests, however, that DM might predispose to more severe gouty arthritis.
Despite its limitations, our study was cross-sectional and subjects were not selected because of a history of back pain. Thus we are confident that axial gout is not rare in patients with moderate to severe chronic gout that has not been optimally controlled with medication. Its presence correlates highly with another marker of severity, namely radiographic erosions and/or tophi in the hands and/or feet. The diagnosis of axial gout can be missed in patients with back pain because, even in patients with known gout, radiographic or magnetic resonance imaging (MRI) studies are more likely to be obtained than CT in the assessment of that clinical problem. However, the changes seen on MRI are generally not specific and do not distinguish gouty erosions and tophi from other pathologies as clearly as does CT5. Further, changes of axial gout can be missed on routine evaluation of spinal CT, as occurred in 50% of our study subjects with clinical gout. If dual-energy CT becomes more widely available and is shown to demonstrate axial tophaceous deposits as clearly as peripheral gouty lesions, then it likely will become the imaging modality of choice for spinal gout.
It is possible that the spinal erosions and tophi will regress with aggressive, effective urate-lowering therapy as can be seen with radiographic gouty changes in the hands and feet17. Definitive evidence for this would require a prospective therapeutic study.
Footnotes
-
Supported in part by a research grant from Savient Pharmaceuticals, Inc. and by a Fellowship Training Award from the Research and Education Foundation, American College of Rheumatology.
- Accepted for publication February 12, 2012.


